Most people who walk into a spine clinic with a slipped disc leave without ever needing an operation. That surprises a lot of first time patients, who arrive already picturing rods, screws and weeks in a hospital bed. In practice, spine surgery in Mohali is usually considered only after rest, physiotherapy and medication have had a fair chance to work, and only when there is a clear medical reason to operate. Knowing what that reason looks like, and what the surgery itself actually involves, makes the decision far less frightening.
When Physiotherapy Stops Working and Surgery Enters the Picture
Most spine problems start the same way: a dull ache that turns into shooting pain down a leg, or stiffness that will not ease with rest. Treatment for spine problems in Mohali almost always follows a step by step approach, moving from the least invasive options toward surgery only if those options fail. Spine treatment plans are built around imaging findings and nerve function, not on symptoms alone.
- Rest and activity modification for the first few weeks, avoiding movements that clearly worsen the pain.
- Physiotherapy and targeted exercises to strengthen the muscles supporting the spine.
- Pain management, including medication or image guided injections for nerve related pain.
- Reassessment with an MRI or nerve function test if symptoms persist beyond six to eight weeks.
- Surgical evaluation, considered only when there is nerve damage, spinal instability, or weakness that keeps getting worse.
Spine surgery is a procedure used to correct problems affecting the vertebrae, discs, or nerves of the spine, such as herniated discs, spinal stenosis, fractures, or instability. It is generally recommended only when nonsurgical treatment fails to relieve pain, or when there are signs of nerve damage, worsening weakness, or loss of bladder or bowel control.
Not every patient with back pain, or even a confirmed slip disc, needs an operation. Many recover fully with slip disc treatment that stays entirely nonsurgical, and surgeons generally recommend continuing conservative care for as long as it keeps helping.
The Different Types of Spine Surgery in Mohali
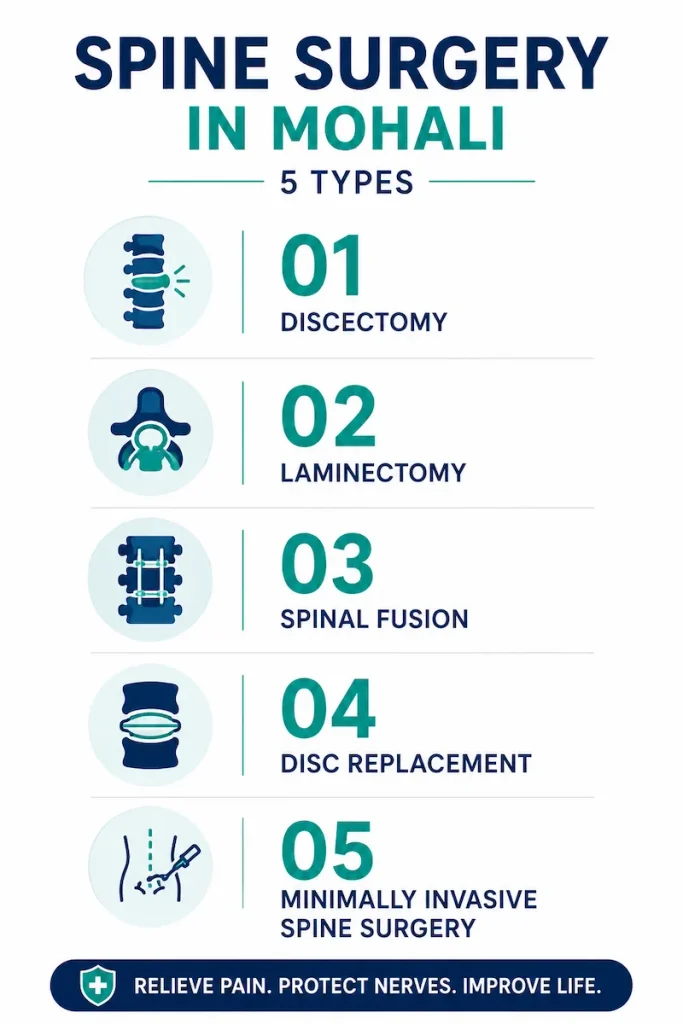
Once nonsurgical treatment has been tried and has not worked, or once red flag symptoms appear, a surgeon will usually recommend one of five broad procedures used in spine surgery in Mohali today. Each is suited to a different problem, and no single technique works for every spine.
- Discectomy: removal of the damaged part of a herniated disc to take pressure off a compressed nerve, commonly used for sciatica that has not improved with physiotherapy.
- Laminectomy: removal of part of the bony arch covering the spinal canal, usually performed for spinal stenosis that is narrowing the space around the nerves.
- Spinal fusion: joining two or more vertebrae into a single solid unit using bone graft and metal implants, used for instability, deformity or advanced degeneration.
- Artificial disc replacement: a prosthesis that replaces a damaged disc while allowing the spine to keep bending and rotating, an alternative to fusion in select cases.
- Minimally invasive spine surgery: smaller incisions and less disruption to muscle, now used for several of the procedures above and often linked to a shorter hospital stay.
Patients with more specific spinal conditions, such as a spinal cord injury, a curve needing scoliosis treatment, or a spinal tumor, are usually managed with a tailored combination of these techniques rather than one standard operation. Chronic nerve pain that has not responded to any of the above is sometimes managed instead with spinal cord stimulation, a separate technique that interrupts pain signals rather than correcting the underlying structure.
Spinal Fusion or Disc Replacement: How the Two Actually Compare
Two questions come up in almost every consultation about fusion surgery: will the spine still move afterward, and how long will recovery take. The two most common answers, fusion and disc replacement, solve the same underlying problem in very different ways.
| Aspect | Spinal Fusion | Disc Replacement |
|---|---|---|
| Effect on spinal movement | Joins two or more vertebrae so that segment no longer moves independently | Preserves motion using a prosthesis that mimics a natural joint |
| Typical recovery | Around 3 to 6 months as the bone gradually fuses | Often quicker, frequently performed as an outpatient or short stay procedure |
| Best suited for | Instability, deformity, spondylolisthesis, advanced degeneration | Single level disc damage in patients with otherwise healthy vertebrae |
| Long term consideration | Extra stress can build on the segments above and below the fusion over time | Requires healthy bone density and joint alignment to work well |
Neither option is automatically better. A surgeon chooses between them based on imaging, the specific vertebrae involved, bone quality and how much of the spine is already affected, not on which technique happens to be newer.
What Recovery Looks Like After Spine Surgery
Recovery after spine surgery depends heavily on which procedure was performed, but a few patterns show up across most patients.
- The first two weeks focus on wound healing, short supervised walks and avoiding bending, twisting or lifting.
- A supportive brace is often used after fusion surgery to protect the area while the bone heals, alongside activity restrictions during this period.
- Physiotherapy usually restarts around four to six weeks, once the surgeon confirms healing is on track.
- Return to desk work often happens within four to eight weeks, while physically demanding jobs generally need longer.
- Clearance for sports, running or heavy lifting is given only after the surgeon reviews follow up imaging and confirms the spine is stable.
A frequent question in follow up visits is simply, when can I play sports again. The honest answer depends on the procedure, the sport, and how the individual spine is healing, which is why surgeons prefer to assess this in person rather than give a fixed date in advance.
Is Spine Surgery Safe? Age, Risks and When Numbness Needs Attention
Spine surgery, like any operation, carries risk, and being open about that is part of an honest consultation rather than a reason to avoid discussing surgery at all. As with any back surgery, patients are generally encouraged to weigh the specific risks against the expected benefit for their own diagnosis.
- Infection at the surgical site, managed through sterile technique and wound care rather than being tied to any particular season.
- Hardware related issues after fusion, such as screws or rods needing later adjustment.
- Lingering numbness or weakness if nerve compression was severe or long standing before surgery.
- General surgical risks such as bleeding or reaction to anaesthesia, discussed individually based on overall health.
Age on its own rarely rules a patient out. What actually matters is bone density, general health and how well other conditions such as diabetes or heart disease are controlled. A patient in their seventies with a spine fracture can be a reasonable surgical candidate once these factors have been properly assessed, just as a much younger patient with poor bone health may need extra caution.
Persistent tingling and numbness in the legs or feet is one of the most common reasons patients seek a spine opinion in the first place. Whether surgery helps depends entirely on the cause. Nerve compression from a disc or from spinal degeneration may respond well to decompression, while numbness caused by a separate condition, such as a nutrient deficiency or diabetes related nerve damage, needs a different kind of evaluation altogether before surgery is even considered.
Finding the Right Spine Surgeon in Mohali
Choosing where to have spine surgery matters just as much as choosing whether to have it. Patients travel in from Chandigarh, Kharar, Zirakpur and Panchkula for the same reason locals in SAS Nagar do, looking for the best spine surgeon in Mohali who is equally comfortable with fusion and with motion preserving techniques, rather than one who defaults to a single procedure regardless of diagnosis.
- Fellowship training in spine surgery, not just general orthopaedics or general neurosurgery.
- A track record with both fusion and non fusion procedures.
- Willingness to explain why surgery is being recommended over continued nonsurgical care.
- Clarity on cost, insurance coverage and what the hospital package actually includes.
A second opinion is a normal part of this process, not a sign of distrust. For broader spine and nerve related concerns beyond surgery alone, our spine specialist in Mohali page and neurosurgeon in Mohali page cover the wider range of conditions assessed before any surgical decision is made.
If back pain, leg pain or numbness has lasted more than a few weeks despite rest and physiotherapy, a focused spine assessment is a reasonable next step. Book a consultation with our spine team in Mohali for a clear, imaging based opinion on what is actually causing the pain.
Key Takeaways
- Surgery is generally the last step after rest, physiotherapy, medication and injections have been tried.
- Discectomy, laminectomy, fusion, disc replacement and minimally invasive techniques each suit a different spinal problem.
- Fusion limits movement at the treated level, while disc replacement is designed to preserve it.
- Recovery ranges from a few weeks for minimally invasive procedures to several months for fusion.
- Age alone does not rule out surgery, overall health and bone quality matter more.
- A second opinion from a fellowship trained spine surgeon is a reasonable step before agreeing to any procedure.
Frequently Asked Questions
1. When is spine surgery actually needed instead of physiotherapy or medication?
Most patients ask this first, and it is a fair question. Treatment for spine problems in Mohali usually starts with rest, physiotherapy and pain management, moving toward surgery only when these options fail to relieve pain or when specific red flags appear. Those red flags include worsening leg weakness, nerve damage confirmed on imaging, spinal instability, or loss of bladder or bowel control. If pain and function stay stable or slowly improve with nonsurgical care, surgery usually is not the next step. A spine specialist can confirm which category a particular case falls into after reviewing symptoms and scans together.
2. What are the different types of spine surgery available?
Spine surgery covers several distinct procedures, each suited to a different problem. Discectomy removes the damaged part of a herniated disc pressing on a nerve. Laminectomy removes bone to relieve pressure in spinal stenosis. Spinal fusion joins two or more vertebrae into one solid unit for instability or deformity. Disc replacement swaps a damaged disc for a prosthesis that preserves movement. Minimally invasive and endoscopic techniques use smaller incisions across several of these procedures, often shortening hospital stay and recovery. A surgeon selects the right option based on imaging, the vertebrae involved and the specific cause of pain, not a single default technique.
3. How much does spine surgery cost, and is it covered by insurance?
This is one of the most common questions we hear, particularly around slip disc surgery and robotic assisted procedures. Cost varies significantly depending on the type of surgery, whether it is open or minimally invasive, the implants used, and the length of hospital stay. Insurance coverage depends entirely on the specific policy, including which procedures and hospitals are included in the network. Patients are generally advised to confirm covered procedures directly with the hospital insurance desk before scheduling surgery, since packages and inclusions can differ even for the same operation. Getting this in writing beforehand avoids confusion later.
4. What is the difference between spinal fusion and disc replacement surgery?
The main difference is what happens to movement at the treated level. Spinal fusion permanently joins the affected vertebrae, so that segment of the spine no longer moves independently, though the rest of the spine continues to function normally. Disc replacement instead uses a prosthesis designed to mimic a natural joint, allowing the spine to keep bending, flexing and rotating at that level. Fusion is generally preferred for instability, deformity or advanced degeneration affecting multiple structures, while disc replacement suits carefully selected single level disc damage. The right choice depends on imaging findings and bone quality, not personal preference alone.
5. How long does recovery take after spine surgery?
Recovery time depends on the procedure. Fusion recovery typically ranges from around three to six months, since the vertebrae need time to gradually grow into a single solid unit, and activity is restricted during this period. Disc replacement, often performed as a minimally invasive or short stay procedure, generally allows a somewhat faster return to daily activity. Physiotherapy usually restarts within four to six weeks for most procedures, once the surgeon confirms healing is progressing as expected. Full return to physically demanding work or sport is cleared individually, based on follow up imaging rather than a fixed calendar date.
6. Can I go back to sports or physical activity after spine surgery?
This is a common concern, and the honest answer is that it depends on the procedure performed and how an individual spine heals. Low impact activity such as walking is usually encouraged early in recovery, while running, contact sports and heavy lifting are reintroduced gradually and only after the surgeon reviews progress. Fusion surgery generally needs a longer wait than minimally invasive discectomy before contact sports are considered safe. Rather than working from a fixed timeline, surgeons prefer to assess strength, stability and imaging results at each follow up visit before clearing a return to a specific activity.
7. Is minimally invasive (endoscopic/keyhole) spine surgery better than open surgery?
Minimally invasive and endoscopic techniques use smaller incisions than traditional open surgery, which generally means less disruption to surrounding muscle, reduced blood loss and a shorter hospital stay in suitable cases. That does not make it automatically better for every patient. Some spinal conditions, particularly complex deformities or multi level instability, still require an open approach for the surgeon to fully correct the problem. The right technique depends on the diagnosis, the number of spinal levels involved and the surgeon’s assessment of what will give the safest, most complete correction for that specific case.
8. Is spine surgery safe for elderly patients (60 years and above)?
Age alone is not automatically disqualifying, including for patients in their seventies with conditions such as a spine fracture. What matters more is overall health, bone density, and how well other conditions like diabetes or heart disease are managed before surgery. Older patients typically go through a more detailed pre surgical evaluation, sometimes involving a physician alongside the spine surgeon, to reduce risk during and after the operation. Many older patients tolerate minimally invasive procedures particularly well, since these involve less blood loss and a shorter recovery period compared with traditional open surgery.
9. Can spine surgery help with numbness, tingling, or weakness in the legs and feet?
These symptoms come up often, and whether surgery helps depends entirely on the underlying cause. When numbness or tingling is caused by a nerve being compressed by a herniated disc or by spinal degeneration, decompression or discectomy can often relieve the pressure and improve symptoms over time. When these symptoms come from an unrelated cause, such as a nutrient deficiency or diabetes related nerve damage, spine surgery will not address them, and a different kind of evaluation is needed instead. An MRI along with nerve function testing usually clarifies which situation applies before any surgery is recommended.
10. How do I choose the right spine surgeon or hospital in Mohali?
Look for a fellowship trained spine surgeon with genuine experience in both fusion and motion preserving procedures, rather than one who defaults to a single technique regardless of diagnosis. Surgeons naturally tend to recommend the approach they perform most often, so a second opinion is a reasonable and normal step, not a sign of distrust. It also helps to ask directly about the hospital’s experience with a specific procedure, its approach to minimally invasive techniques, and how clearly the team explains cost and insurance coverage before surgery. A clear, unhurried explanation of the diagnosis is usually a good sign.
Back and leg pain rarely needs surgery on day one, but ignoring red flag symptoms for months carries its own risk. Whether the right next step is continued physiotherapy or a proper surgical evaluation, getting an accurate diagnosis first is what actually protects the spine. For patients across Mohali, SAS Nagar, Chandigarh and the wider Punjab region, a focused conversation about spine surgery in Mohali with a fellowship trained specialist is usually the clearest way to find out which category a particular case falls into.